Vaginal Cancer

Key points
- Vaginal cancer accounts for 1% of gynecologic malignancies in the USA.
- The most common complaint is abnormal vaginal bleeding, which may be postcoital, intermenstrual, or postmenopausal.
- The 5-yr survival is related to stage (stage I, 65 to 70%; stage II, 47%; stage III, 30%; stage IV, 15 to 20%).
- Most (95%) vaginal malignancies are squamous cell carcinomas.
Vaginal cancer accounts for 1% of gynecologic malignancies in the USA. Average age at diagnosis is 60 to 65 yr. Patients with a history of human papillomavirus infection or of cervical or vulvar cancer are at increased risk. Exposure to diethylstilbestrol in utero is associated with the development of clear cell adenocarcinoma of the vagina in young women; mean age at diagnosis of this rare malignancy is 19 yr.
Most (95%) vaginal malignancies are squamous cell carcinomas. The remainder include primary and secondary adenocarcinomas, secondary squamous cell carcinoma (in older women), clear cell adenocarcinomas (in young women), and melanoma. The most common vaginal sarcoma, sarcoma botryoides (embryonal rhabdomyosarcoma), has a peak incidence at age 3.
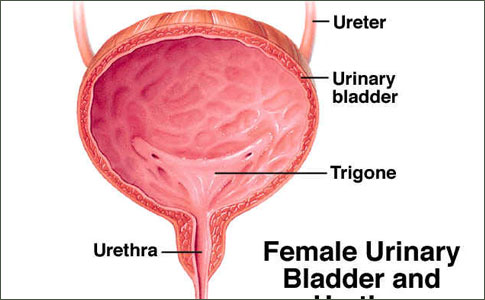
Vaginal cancer may spread by direct extension into the local paravaginal tissues, bladder, or rectum; through inguinal lymph nodes from lesions in the lower vagina; through pelvic lymph nodes from lesions in the upper vagina; or hematogenously.
Symptoms and Signs
The most common complaint is abnormal vaginal bleeding, which may be postcoital, intermenstrual, or postmenopausal. Patients may also present with a watery vaginal discharge or dyspareunia. Vesicovaginal or rectovaginal fistulae are late manifestations of vaginal cancer. A few patients are asymptomatic; a lesion may be discovered during a routine pelvic examination, or a Pap smear may be abnormal.
A punch biopsy usually yields a diagnosis, but occasionally wide local excision using an anesthetic is necessary. Most lesions occur in the upper 1/3 of the vagina on the posterior wall. The staging system is clinical, primarily based on the physical examination, endoscopy, and skeletal x-rays (see Table 241-6).
Prognosis and Treatment
The 5-yr survival is related to stage (stage I, 65 to 70%; stage II, 47%; stage III, 30%; stage IV, 15 to 20%). Adverse prognostic factors include large primary tumor size and poorly differentiated tumors. Treatment depends on the location and stage of the disease. For most primary vaginal tumors, treatment with radiation, usually a combination of external beam and brachytherapy, is best. For a small vaginal tumor localized to the upper 1/3 of the vagina, radical hysterectomy with upper vaginectomy and pelvic lymph node dissection may be used. If radiation therapy is contraindicated because of vesicovaginal or rectovaginal fistulas, primary pelvic exenteration is performed.
Written and revised by
Andrey Nailor, M.D.
Our doctors write and review articles for accuracy and keep them up to date.
health.am provides general information, not medical advice. Always consult a qualified health professional about your own health.
Explore health topics
More in this topic
Cancer → Guide
New method for better treatment of breast cancer
A new study shows that a novel imaging-based method for defining appropriateness of breast cancer treatment is as accurate as the current standard-of-care and could reduce the need for invasive tissue sampling. The…
31 December 2015
 News
T cells that recognize HER2 teceptor may prevent HER2+ breast cancer recurrence
Recurrence of HER2-positive breast cancer after treatment may be due to a specific and possibly cancer-induced weakness in the patient's immune system - a weakness that in principle could be corrected with a…
31 December 2015
 News
New breast cancer drug may be effective against other types of cancer
Palbociclib, a new oral drug whose efficacy in combating breast cancer has been demonstrated alone and in combination with endocrine therapy, also has potential to combat other types of cancer, according to a literature…
30 December 2015