Sigmoidoscopy an option for colon cancer screening
David Cohen, M.D.·Published 21 May 2012·10 min read
Key points
Screening for colon cancer using a flexible tube - which is less invasive and more convenient than colonoscopy - may also help prevent new cases and deaths from the disease, a new study suggests.
You should begin screening for colorectal cancer soon after turning 50, then continue getting screened at regular intervals.
Flexible sigmoidoscopy utilizes a flexible sigmoidoscope, a flexible, fiberoptic viewing tube with a light at the tip.
The screening tests were not without their limitations.
Screening for colon cancer using a flexible tube - which is less invasive and more convenient than colonoscopy - may also help prevent new cases and deaths from the disease, a new study suggests.
In a large trial of more than 150,000 older U.S. adults, those who were randomly assigned to get screened using so-called flexible sigmoidoscopy on two different occasions were 21 percent less likely to get colon cancer than those not offered the screening.
They were also 26 percent less likely to die of cancer, probably because screening picked up pre-cancerous lesions and early-stage cancers before they could cause serious harm, researchers reported Monday in the New England Journal of Medicine.
Colonoscopy "is a very unpleasant thing," said Dr. Alfred Neugut, an epidemiologist and oncologist from Columbia University in New York, who wasn't part of the study team.
"Sigmoidoscopy is a much less elaborate procedure, so you can basically walk into the doctor's office and get it on the spot… and it's much less invasive," he said.
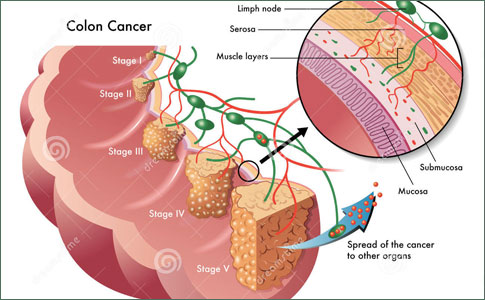
Screening Saves Lives Colorectal cancer almost always develops from precancerous polyps (abnormal growths) in the colon or rectum. Screening tests can find precancerous polyps, so that they can be removed before they turn into cancer. Screening tests can also find colorectal cancer early, when treatment works best.
When Should I Begin to Get Screened?
You should begin screening for colorectal cancer soon after turning 50, then continue getting screened at regular intervals. However, you may need to be tested earlier than 50 or more often than other people if—
- You or a close relative have had colorectal polyps or colorectal cancer. - You have inflammatory bowel disease. - You have genetic syndromes such as familial adenomatous polyposis (FAP) or hereditary non-polyposis colorectal cancer.
Speak with your doctor about when you should begin screening and how often you should be tested.
Flexible sigmoidoscopy is one of three colon cancer screening methods recommended by the U.S. Preventive Services Task Force, a government-backed body that sets screening guidelines.
Flexible sigmoidoscopy
Flexible sigmoidoscopy utilizes a flexible sigmoidoscope, a flexible, fiberoptic viewing tube with a light at the tip. It is inserted through the anus and is used by the doctor to examine the rectum and the part of the colon adjacent to the rectum. It is a shorter version of a colonoscope. Approximately 50% of colorectal cancers and polyps are found to be within the reach of a flexible sigmoidoscope. It is recommended that individuals of average risk for colon cancer undergo a flexible sigmoidoscopy examination at age 50 and every 3-5 years thereafter. If polyps are found during a flexible sigmoidoscopic examination, a colonoscopy to examine the entire colon is recommended to remove the polyps as well as to find and remove additional polyps in other parts of the colon. The removed polyps are examined by a pathologist under a microscope to determine if the polyps are benign, malignant or pre-cancerous. Individuals with precancerous polyps (adenomas and villous adenomas) have a higher than average risk of developing colon cancer, and it is recommended that they return periodically for surveillance colonoscopies.
Written and revised by
David Cohen, M.D.
Our doctors write and review articles for accuracy and keep them up to date.
health.am provides general information, not medical advice. Always consult a qualified health professional about your own health.
The Task Force says that annual fecal occult blood testing, flexible sigmoidoscopy every five years with fecal testing every three years or colonoscopy every 10 years are all options for adults aged 50 to 75 at average risk of cancer.
But many Americans in that age group still don't get screened - and one of the reasons may be the discomfort of preparing to get a colonoscopy, including taking laxatives, and the inconvenience and invasiveness of the procedure itself.
What is the best colon cancer screening test? Colonoscopy is the only method that has a high sensitivity for all polyps - small and large - and that can remove them during the procedure. CT colonography or virtual colonoscopy can miss small or flat lesions but has the advantage of being less invasive. It still requires a complete bowel cleansing prior to the procedure. If an abnormality is seen during virtual colonoscopy, a colonoscopic examination will still be needed to verify the finding or for polyp removal. Other, newer screening procedures include testing for abnormal DNA in the stool or the combination of a flexible sigmoidoscopy and a barium enema. The barium enema is suggested if colonoscopy is not available. However, for the removal of polyps, there is only one procedure that is currently useful, and that is colonoscopy.
Are colorectal screening tests done by your general practitioner or should they be done by gastroenterologists or other experts? There are several types of colorectal cancer screening tests. Fecal occult blood tests (FOBT) are usually provided by your general practitioner for you to take home and then return to the laboratory for development and analysis. Flexible sigmoidoscopy, which evaluates the lower third of the colon with an endoscope, is performed by some but not all general practitioners. Colonoscopy is a more extensive endoscopic evaluation of the entire length of the colon and is generally done by gastroenterologists or other gastrointestinal specialists. Colonoscopy is considered the gold standard for colorectal cancer screening by the American Cancer Society and many more professional organizations. It is highly recommended that your primary care provider refer you to a board-certified gastroenterologist or endoscopist to have the test done.
The new findings provide more evidence that sigmoidoscopy as an initial test - followed by colonoscopy only in the case of positive findings - may be a valid alternative, researchers said.
The data come from the Prostate, Lung, Colorectal, and Ovarian (PLCO) Cancer Screening Trial, which compared new cases of cancer and cancer-related deaths in adults who did or didn't get different types of screening.
{pagebreak}
This analysis, led by Dr. Robert Schoen from the University of Pittsburgh Medical Center, involved 154,900 adults age 55 to 74 who were offered either two sigmoidoscopies, three or five years apart, or no colon cancer screening.
Over the next 12 years, there were 1,012 new cases of colon cancer in the screening group and 1,287 in the unscreened group. In addition, there were 252 related deaths among people offered sigmoidoscopy, compared to 341 in the unscreened group.
The lower mortality in the screening group seemed to be attributable entirely to fewer deaths from so-called distal colon cancer, which occurs in the part of the intestines closer to the rectum. There was no difference between the two groups in deaths from proximal colon cancer, which is cancer higher up in the intestines and beyond the reach of the sigmoidoscopy scope.
How many people are being screened for colorectal cancer? Unfortunately, screening rates are too low. In a recent survey of Americans over 50 conducted by the Centers for Disease Control, only 41percent reported having had either an FOBT (the take-home stool card test) or a partial colon exam (by sigmoidoscopy) within the time intervals recommended by major professional groups such as ASGE. Given the preventable nature of this cancer, we can and must do better! For comparison, 86 percent of women are screened for breast cancer. The American Cancer Society has a goal for 75 percent of adults aged 50 and over to get screened by 2015.
Some reasons for low colorectal cancer screening rates include: - Lack of public awareness about colorectal cancer and the benefits of regular screening - Inconsistent promotion of screening by medical care providers - Uncertainty among healthcare providers and consumers about insurance benefits - Characteristics of the screening procedures (e.g., imperfect tests, negative attitudes towards the screening procedures) - Hesitance to discuss "the disease down there"
FALSE POSITIVES COMMON
The screening tests were not without their limitations. One in five men and one in eight women had a false-positive sigmoidoscopy, which resulted in more invasive testing that ultimately found no pre-cancers or cancers. In addition, 22 people suffered a bowel perforation either from the initial sigmoidoscopy or a follow-up colonoscopy.
A limitation of the trial itself is that the two study groups weren't as different as the researchers initially intended: almost half of people in the group assigned to no screening ended up getting a sigmoidoscopy or colonoscopy on their own during the study.
Trials in the UK and Italy have also suggested screening with sigmoidoscopy can reduce deaths from colon cancer.
Because of that, the UK plans to offer sigmoidoscopies free of charge to all adults in their mid-50s within the next five years, according to Wendy Atkin, a professor of gastrointestinal epidemiology at Imperial College London, who worked on the UK study.
"We need to revisit sigmoidoscopy in the United States," Atkin told Reuters Health.
Flexible sigmoidoscopy
During this test, the doctor looks at part of the colon and rectum with a sigmoidoscope - a flexible, lighted tube about the thickness of a finger with a small video camera on the end. It is inserted through the rectum and into the lower part of the colon. Images from the scope are viewed on a display monitor.
Using the sigmoidoscope, your doctor can view the inside of the rectum and part of the colon to detect (and possibly remove) any abnormality. Because the sigmoidoscope is only 60 centimeters (about 2 feet) long, the doctor is able to see the entire rectum but less than half of the colon with this procedure.
Before the test: You will need to have a bowel preparation to clean out your lower colon. The colon and rectum must be empty and clean so your doctor can view the lining of the sigmoid colon and rectum. Your doctor will give you specific instructions to follow. You may be asked to follow a special diet (such as drinking only clear liquids) for a day before the exam. You may also be asked to use enemas or to use strong laxatives to clean out your colon before the exam. Be sure your doctor is aware of any medicines you are taking, as you may need to change how you take them before the test.
During the test: A sigmoidoscopy usually takes 10 to 20 minutes. Most people do not need to be sedated for this test, but this may be an option you can discuss with your doctor. Sedation may make the test less uncomfortable, but it requires some time to recover from it, as well as having someone with you to take you home after the test.
You will likely be asked to lie on a table on your left side with your knees positioned near your chest. Your doctor should do a digital rectal exam, or DRE (inserting a gloved, lubricated finger into the rectum), before inserting the sigmoidoscope. The sigmoidoscope is lubricated to make it easier to insert into the rectum. The scope may feel cold. The sigmoidoscope may stretch the wall of the colon, which may cause bowel spasms or lower abdominal pain. Air will be placed into the sigmoid colon through the sigmoidoscope so the doctor can see the walls of the colon better. During the procedure, you might feel pressure and slight cramping in your lower abdomen. To ease discomfort and the urge to have a bowel movement, it helps to breathe deeply and slowly through your mouth. You will feel better after the test once the air leaves your colon.
If a small polyp is found during the test your doctor may remove it with a small instrument passed through the scope. The polyp will be sent to a lab to be looked at by a pathologist. If a pre-cancerous polyp (an adenoma) or colorectal cancer is found during the test, you will need to have a colonoscopy at a later date to look for polyps or cancer in the rest of the colon.
Possible complications and side effects: This test may be uncomfortable because of the air put into the colon, but it should not be painful. Be sure to let your doctor know if you feel pain during the procedure. You might see a small amount of blood in your first bowel movement after the test. Significant bleeding and puncture of the colon are possible complications, but they are very uncommon.
Research suggests nurses can do the less-invasive test, she said. It's also significantly cheaper than colonoscopy - at roughly $150, compared to about $1,000 for a colonoscopy.
Schoen doesn't expect colonoscopy to go out of style as the most popular method for colon cancer screening in the U.S. But, he added, flexible sigmoidoscopy as an initial test is a good choice for some people who want to avoid a colonoscopy unless it's completely necessary.
"Absolutely it's an option on the table," he told Reuters Health.
"If someone, for example, was afraid of anesthesia, if they want a test where the prep is not so aggressive - they just take enemas as opposed to drinking laxatives, if they cannot spare a day… all those are good reasons if you want to go and have a (sigmoidoscopy)," Schoen said.
Neugut told Reuters Health many U.S. doctors don't do the less-invasive procedures anymore. But data are lacking to prove colonoscopy is any better than initially going for sigmoidoscopy, he said.
"Anyone who doesn't want to have a colonoscopy, they should consider sigmoidoscopy as certainly… a valid form of screening for colon cancer," Neugut said.


 News
 News
 News