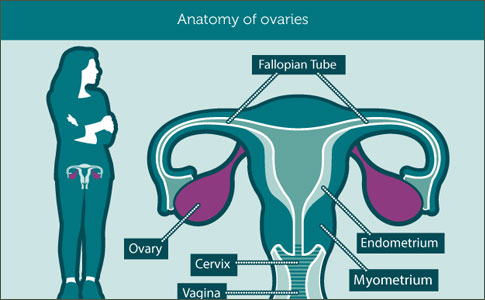
Study Explains High Platelets in Ovarian Cancer Patients; Survival Reduced
Andrey Nailor, M.D.·Published 17 February 2012·9 min read
Key points
Highly elevated platelet levels fuel tumor growth and reduce the survival of ovarian cancer patients, an international team of researchers led by scientists at The University of Texas MD Anderson Cancer center reports in the New England Journal of Medicine.
High platelet counts often occur due to an underlying medical condition.
Some people might be at a significantly higher risk of developing high platelet levels within the blood.
"This research comes from clinical observations," Sood said.
Highly elevated platelet levels fuel tumor growth and reduce the survival of ovarian cancer patients, an international team of researchers led by scientists at The University of Texas MD Anderson Cancer center reports in the New England Journal of Medicine.
By pinpointing a powerful cause-and-effect relationship at the heart of a clinical observation that dates back more than 100 years, the team's findings reveal a new factor in cancer progression and new potential approaches for treatment.
"We've long known that ovarian cancer patients often have markedly increased platelet counts but we haven't known why this happens or understood its relevance, if any, to disease progression," said senior author Anil Sood, M.D., professor in MD Anderson's Departments of Gynecologic Oncology and Reproductive Medicine and Cancer Biology.
"Our collaborative study not only identified a mechanism that explains platelet count elevation, but also connects this state, called thrombocytosis, to the severity of ovarian cancer," Sood said. "This suggests drugs that interfere with coagulation might be a useful addition to conventional therapies."
Tumor makes IL-6, liver produces TPO, platelets abound, tumor grows
Drawing on clinical data from ovarian cancer patients and following up with mouse model experiments and a clinical trial, Sood and colleagues discovered:
High platelet counts often occur due to an underlying medical condition. Many people with thrombocytosis also have cancer, especially ovarian gastrointestinal, ovarian and lymphoma. In many cases, high platelet counts are considered to be an initial cancerous sign.
Risk
Some people might be at a significantly higher risk of developing high platelet levels within the blood. These people include those who have recently undergone any type of surgical procedure, and those who have iron-deficiency anemia.
* Ovarian cancers produce the inflammatory cytokine interleukin-6 (IL-6); * Triggering creation of the platelet-production regulating hormone thrombopoietin (TPO) in the liver; * Causing platelet counts to soar to more than 450,000 per cubic millimeter in the blood, the threshold for thrombocytosis, and * Stimulating tumor growth and continuation of the cycle.
"Platelets may function as a fuel depot for tumors by providing them with growth factors," Sood said. They were found not only in the blood but also in the tumor's microenvironment, in the tumor bed, and in ascites, fluid build-up in the abdominal cavity common in ovarian cancer.
THE ROLE OF PLATELETS IN OVARIAN CARCINOMA Platelets represent one of the largest storage pools of angiogenic and oncogenic growth factors in the human body. The observation that thrombocytosis (platelet count >450,000/uL) occurs in patients with solid malignancies was made over 100 years ago. However, the clinical and biological implications as well as the underlying mechanism of paraneoplastic thrombocytosis associated with ovarian carcinoma remains unknown and were the focus of the current study.
Written and revised by
Andrey Nailor, M.D.
Our doctors write and review articles for accuracy and keep them up to date.
health.am provides general information, not medical advice. Always consult a qualified health professional about your own health.
Following IRB approval, patient data were collected on 619 patients from 4 U.S. centers and used to test associations between platelet count at initial diagnosis, clinicopathologic factors, and outcome. In vitro effects of plasma-purified platelets on ovarian cancer cell proliferation, docetaxel-induced apoptosis, and migration were evaluated using BrdU-PI flow cytometric and two-chamber chemotaxis assays. In vivo effects of platelet depletion on tumor growth, proliferation, apoptosis, and angiogenesis were examined using an anti-platelet antibody (anti-mouse glycoprotein 1ba, Emfret) to reduce platelets by 50%. Complete blood counts and number of mature megakaryocytes in the spleen and bone marrow were compared between control mice and ovarian cancer-bearing mice. Plasma levels of key megakaryo- and thrombopoietic factors including thrombopoietin (TPO), IL-1a, IL-3, IL-4, IL-6, IL-11, G-CSF, GM-CSF, stem cell factor, and FLT-3 ligand were assayed in a subset of 150 patients at the time of initial diagnosis with advanced stage, high grade epithelial ovarian cancer using immunobead-based cytokine profiling coupled with the Luminex® xMAP platform. Plasma cytokines significantly associated with thrombocytosis in ovarian cancer patients were subsequently evaluated in mouse models of ovarian cancer using ELISA immunoassays. The results of human and mouse plasma cytokine profiling were used to inform subsequent in vivo studies evaluating the effect of siRNA-induced silencing of select megakaryo- and thrombopoietic cytokines on paraneoplastic thrombocytosis. ###
Rebecca L. Stone, University of Texas Graduate School of Biomedical Sciences at Houston
In a clinical trial conducted at the Barts Cancer Institute, Queen Mary, University of London, the team also found that treatment of 18 ovarian cancer patients in a phase I/II clinical trial with siltuximab, an antibody to IL-6, sharply reduced platelet counts over a three-week period.
Clinical observation leads to survival connection
"This research comes from clinical observations," Sood said. "We have many ovarian cancer patients with thrombocytosis and decided to look into the causes for it."
The crux of the research was nicely summed in the MD Anderson press release:
“Highly elevated platelet levels fuel tumor growth and reduce the survival of ovarian cancer patients.”
A literature search revealed that the association between what was then called a "hyper-coagulable state" and cancer was noted as far back as 1867, but no relationship between the two had been established.
Of 619 ovarian cancer patients, 192 (31 percent) had thrombocytosis. Importantly, less than 2 percent of those had an iron deficiency or a non-cancerous inflammatory condition, the two most common causes of elevated platelet levels.
Patients with thrombocytosis survived for a median of 2.62 years, compared to 4.65 years for those with normal platelet counts. After accounting for age, disease stage, tumor grade and type and the extent of surgical tumor reduction, thrombocytosis remained an independent predictor of poor survival.
{pagebreak}
Tracking down cause and effect
The team found elevated platelet counts in three separate mouse models of epithelial ovarian cancer and in pancreatic and uterine cancer models, but not breast cancer.
They also found a connection between high platelet counts and higher levels of large cells called megakaryocytes, which occur in the bone marrow and fragment into platelets under the direction of thrombopoietin.
Next, in a cohort of 150 ovarian cancer patients, they analyzed plasma levels of 10 factors in the blood known to regulate creation of megakaryocytes. Again, 31 percent had thrombocytosis.
Levels of interleukin-6 and thrombopoietin in blood serum were substantially elevated in patients with thrombocytosis. A separate analysis of 310 ovarian cancer patients showed that elevated IL-6 is also associated with reduced progression-free survival.
When oncologists see patients with high platelet levels do they currently treat them in any way?
Dr Sood: Not really any differently. It is something that we have simply known for a long time. In this context, given especially that these patients tend to have aggressive behavior (of the tumour), there is a lot of potential clinical implications, but again this is relatively new, so I think we need to do additional work to really figure out what are the best approaches to treat these patients.
Is it better to combine an IL-6 antibody, specially in those patients who have high platelets, along with chemotherapy? Can drugs like even aspirin or things like that that interfere with platelet function, could those have implications? There are data that would suggest that patients who are on a daily aspirin tend to live longer in the context of cancer patients. These type of things need to be developed further.
Blocking thrombopoietin and interleukin-6 reduces platelets, shrinks tumors
To understand the functional role TPO and IL-6 play in raising platelet levels, the researchers used short interfering RNA to shut them down separately and together in mice. In each case, platelet levels fell steeply, with thrombocytosis completely eliminated when both IL-6 and TPO were silenced.
To test IL-6 as a target, they treated two strains of mice with ovarian cancer with the IL-6 antibody siltuximab, paclitaxel chemotherapy, or both. All three treatments reduced platelet count and tumor burden. The combination was most effective, reducing tumor growth by 90 percent.
Treatment of mice with an anti-platelet antibody cut both the circulating platelet count and average tumor size in half, reduced cell proliferation by 44 percent and tumor blood vessel density by 51 percent.
More to study: precise mechanisms, potential treatments
While the researchers note that platelets are likely to promote cancer growth by strengthening tumor blood vessels, the precise mechanisms involved remain to be discovered via prospective collection and in-depth analysis of platelets from cancer patients.
The authors note their findings might explain why some blood-thinning agents improve survival in some cancer patients independent of their prevention of vascular blood clotting, and why daily use of aspirin after diagnosis of colorectal cancer also improved survival in a prospective clinical trial.
Platelet levels may also serve as biomarkers for ovarian and other cancers, Rebecca Stone, M.D., clinical fellow in gynecologic oncology and the first author of the study, noted. "If you see high platelets, absent inflammation or iron deficiency, it would be important to look for cancer."
MD Anderson co-authors with Sood and first author Stone are Alpa Nick, M.D., Hee Dong Han, Ph.D., Justin Bottsford-Miller, M.D., Wei Hu, M.D., Ph.D., Hannah Gershenson, Koji Matsuo, M.D., Mian M.K. Shahzad, M.D., Erin R. King, M.D., of the Department of Gynecologic Oncology; Rajesha Rupaimoole of the Department of Cancer Biology; Guillermo N. Armaiz-Pena, Ph.D., Ibrahim Tekedereli, M.D., Bulent Ozpolat, M.D., Ph.D., and Gabriel Lopez-Berestein, M.D., of the Department of Experimental Therapeutics; Chad Pecot, M.D., Division of Cancer Medicine; Michael Deavers, M.D., of the Department of Pathology; Hernan Vasquez, Ph.D., and Vahid Afshar-Kharghan, M.D., of the Section of Benign Hematology; Diana Urbauer of the Department of Biostatistics and Francisca Gushiken, M.D., of the Department of Leukemia. Sood, Han and Lopez-Berestein also are with the Center for RNA Interference and Non-Coding RNA. Lopez-Berestein also is affiliated with the Department of Nanomedicine and Bioengineering at The University of Texas Health Science Center at Houston.
Collaborating co-authors are Iain McNeish, Ph.D., Frances Balkwill, Ph.D., and Jermaine Coward, Ph.D. of the Barts Cancer Institute, Queen Mary, University of London; Charles Landen, M.D., Department of Obstetrics and Gynecology, University of Alabama, Birmingham; Edward H. Ahn, M.D., and Virginia K. Bond, M.D., of the Department of Obstetrics and Gynecology, University of Maryland, Baltimore; Rui Wang and Wah Chiu, Ph.D., of the Department of Biochemistry and Molecular Biology, Baylor College of Medicine; Angela F. Drew, Ph.D., of the Department of Cancer and Cell Biology, University of Cincinnati; and from the University of Iowa Katherine Collins, Department of Psychology, Koen DeGeest, M.D., of the Department of Obstetrics and Gynecology; and Susan Lutgendorf, Ph.D., of the Departments of Psychology, Urology, Obstetrics and Gynecology and the Holden Comprehensive Cancer Center.
Funding Sources
Funding for this research was provided by Gail MacNeil KOH Research Award from the Gynecologic Cancer Foundation; grants from the National Cancer Institute, a Program Project Development Grant from the Ovarian Cancer Research Fund; the U.S. Department of Defense; the Baylor College of Medicine and M.D. Anderson Cancer Center Multidisciplinary Research Program; the Anne and Henry Zarrow Foundation; the Marcus Foundation, Inc.; the estate of C.G. Johnson, Jr.; the United Kingdom Medical Research Council; the Blanton-Davis Ovarian Cancer Research Program; the Laura and John Arnold Foundation; the RGK Foundation; the Bettyann Asche Murray Distinguished Professorship in Ovarian Cancer Research; and NCI training grants.
About MD Anderson
The University of Texas MD Anderson Cancer Center in Houston ranks as one of the world's most respected centers focused on cancer patient care, research, education and prevention. MD Anderson is one of only 40 comprehensive cancer centers designated by the National Cancer Institute. For eight of the past 10 years, including 2011, MD Anderson has ranked No. 1 in cancer care in "Best Hospitals," a survey published annually in U.S. News & World Report.
###
Source: University of Texas M. D. Anderson Cancer Center


 News
 News
 News